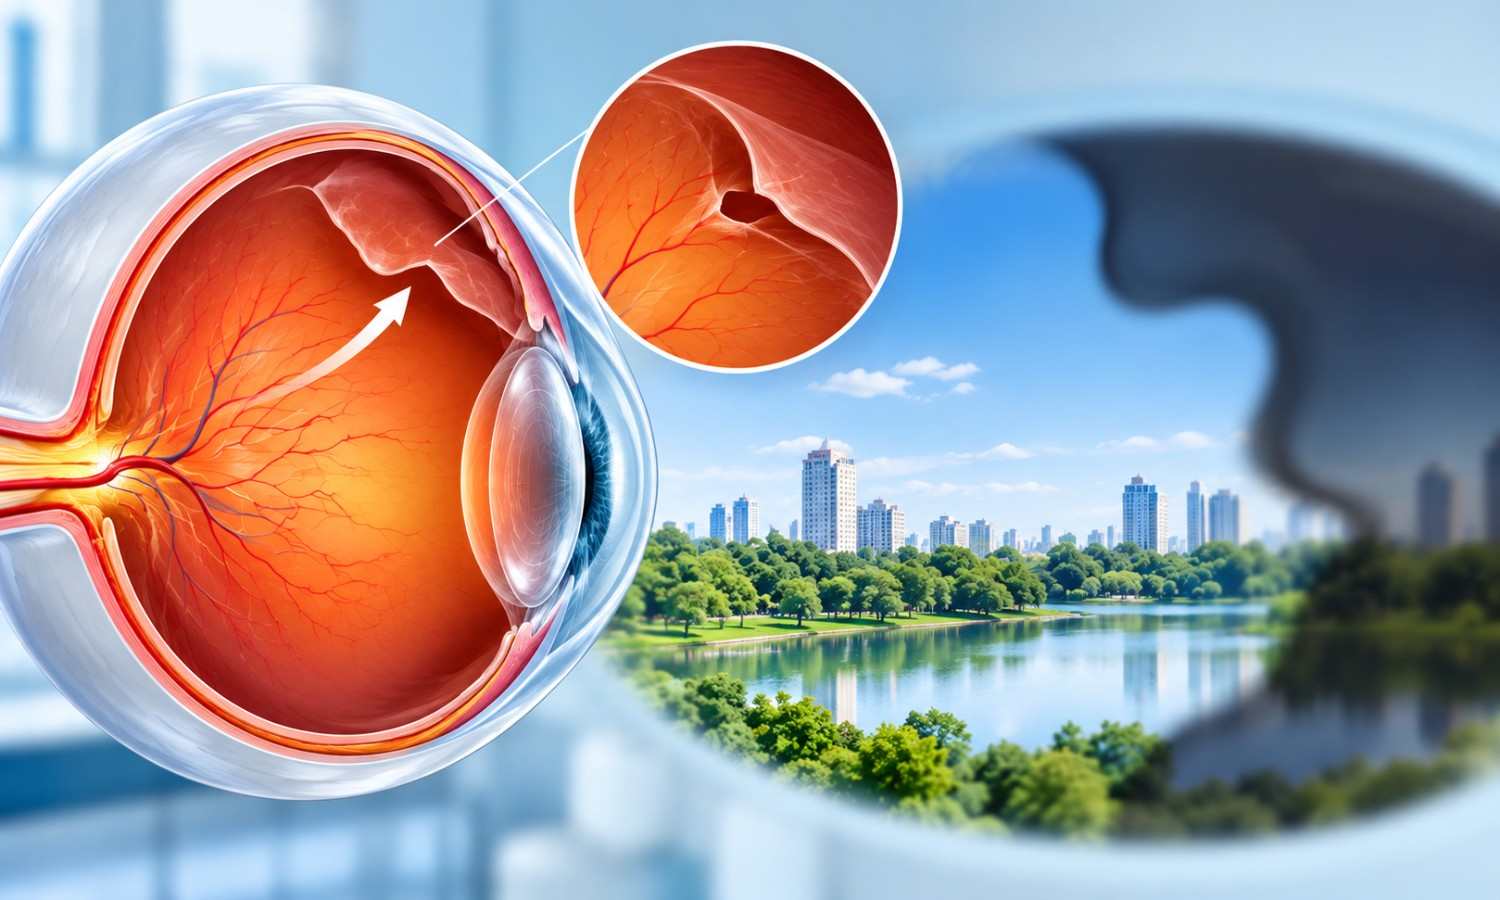
Retinal Detachment: Warning Signs, Emergency Treatment and When to See a Retina Specialist
The retina is
the thin, light-sensing layer at the back of your eye. In retinal detachment,
it pulls away from the tissue that supports and nourishes it. The longer it
stays detached, the greater the risk of permanent vision loss, which is why
doctors treat it as an emergency. It usually causes no pain, so changes in your
vision are the main warning.
This article
explains the warning signs, what to do if you suspect a detachment, causes and
risk factors, diagnosis, treatment, and how to choose between emergency eye
care and a retina specialist visit. Floaters and flashes have many harmless
causes, and only an eye examination can tell which one you have.
What Is Retinal Detachment?
The retina
captures light and sends signals to the brain, which turns them into the images
you see. It depends on the layer beneath it for blood supply. When the retina
separates from that layer, the detached area stops working properly, and
central or side vision can be lost.
A retinal
tear is a break in the retina. A retinal detachment happens when
fluid passes through a tear and lifts the retina away. Most retinal tears do
not lead to detachment, but a tear that causes symptoms carries a high risk, so
it is usually treated promptly. This is the most common type, called
rhegmatogenous detachment. Less often, scar tissue pulls the retina away
(tractional, for example in advanced diabetic eye disease), or fluid collects
beneath it without a tear (exudative).
Prompt
treatment matters because the retina cannot function without its support layer.
If the macula, the central area that gives sharp vision, is still attached,
early repair gives the best chance of protecting it.
What Are the Warning Signs of Retinal Detachment?
Symptoms often
come on quickly. They can appear before a detachment develops or as it spreads.
A sudden increase in floaters
Floaters are
small dark spots, threads or cobweb shapes that drift across your vision. A few
are common. A sudden shower of new floaters, or a sudden rise in their number,
can mean a retinal tear, sometimes with bleeding inside the eye.
Flashes of light
New flashes of
light in one or both eyes may happen when the gel inside the eye tugs on the
retina. They are most concerning when they are new, or appear together with new
floaters.
A curtain or shadow over your vision
A dark curtain,
veil or shadow spreading in from the side or the middle of your vision is a
classic sign that the retina is detaching. Blinking or rubbing your eye does
not clear it.
Blurred or reduced vision
Vision may
become suddenly blurred, distorted or dimmer, particularly if the macula is
involved.
Loss of peripheral vision
Side vision can
fade first, so you may not notice until the missing area grows. Covering one
eye at a time may reveal a gap, but a normal-looking result does not rule out a
problem.
Symptoms can
be subtle, and there is usually no pain. Some tears or detachments cause
only a few new floaters or a small shadow at first. Most floaters and flashes
come from the gel inside the eye separating from the retina, called posterior
vitreous detachment. That is common and often harmless, but it can sometimes
tear the retina. Symptoms alone cannot tell the difference, so a dilated
examination is needed.
What Should You Do If You Suspect Retinal Detachment?
•
Get examined the same day. Call an eye hospital
or ophthalmologist and say you have symptoms of a possible retinal detachment.
If you cannot be seen promptly, go to the nearest hospital emergency
department.
•
Do not wait for symptoms to settle. They may
fade while the problem continues.
•
Do not delay for an online checklist, advice
from friends or a home remedy. None of these can rule out a detachment.
•
Arrange a lift. Avoid driving if your vision is
affected, and ask someone to go with you.
•
Carry what you can quickly: your glasses, a list
of medicines and any earlier eye reports, and note when the symptoms began. Do
not delay leaving to collect them.
If you have
already been checked and your symptoms change or come back, get examined again
straight away.
What Causes Retinal Detachment?
Most
detachments begin with changes in the vitreous, the clear gel that fills the
eye. With age, the gel becomes more liquid and can pull away from the retina.
This is usually harmless, but sometimes it pulls hard enough to cause a tear.
Fluid can then pass through the tear and lift the retina. Other mechanisms
include:
•
Retinal tears or holes, including thin areas of
the peripheral retina such as lattice degeneration.
•
Significant eye injury.
•
Traction from scar tissue, for example in
advanced diabetic eye disease.
•
Fluid beneath the retina without a tear, which
can follow some inflammatory or other eye conditions.
A risk factor
raises the chance of detachment, but it is not a certain cause. Many people
with risk factors never develop one.
How Is Retinal Detachment Diagnosed?
A dilated
retinal examination is the key test. Drops widen the pupil so the
ophthalmologist can examine the whole retina, including its outer edges, for
tears or detachment. If blood or a dense cataract blocks the view, an
ultrasound scan (B-scan) can show whether the retina is detached. Retinal
photography or optical coherence tomography (OCT) may be used to record
findings or assess the macula.
Which tests are
used depends on your symptoms and what the doctor sees, and not everyone needs
every test. The drops can blur your vision for a few hours, so bring a
companion.
What Are the Treatment Options for Retinal Detachment?
Treatment
depends on the location, size and severity of the tear or detachment, whether
the macula is involved, and the condition of the eye. The procedures are not
interchangeable, and not every patient needs the same one.
•
Laser treatment or cryotherapy (freezing) can
seal selected retinal tears so fluid cannot pass through them.
•
Pneumatic retinopexy uses a gas bubble injected
into the eye, together with freezing or laser, to press a tear closed. It is
suitable only for selected detachments, and head positioning afterwards is
important.
•
Scleral buckle surgery places a flexible band on
the outer wall of the eye to push it gently toward the tear, usually with
freezing or laser to seal the tear.
•
Vitrectomy removes the vitreous gel pulling on
the retina, repositions the retina and seals it, usually with a temporary gas
bubble or silicone oil. If gas is used, air travel and high altitudes must be
avoided until it is absorbed.
Some eyes need
further treatment. Your surgeon will explain which approach suits your eye and
what to expect.
Can Retinal Detachment Cause Permanent Vision Loss?
Yes. Without
treatment, vision in the affected eye deteriorates, and the longer the retina
stays detached, the greater the risk of permanent loss. Outcomes depend on how
much of the retina is detached, for how long, whether the macula was involved,
and other eye conditions. Surgery usually stops vision getting worse, and
treatment works well when the problem is found early. Even so, recovery cannot
be guaranteed: vision may not return fully, and some people need more than one
operation. Ask your surgeon what to expect for your eye.
Who Is at Higher Risk of Retinal Detachment?
•
A previous retinal detachment in one eye (the other eye
can also be affected).
•
A family history of retinal detachment.
•
Significant short-sightedness (myopia).
•
Previous eye surgery, including cataract surgery.
•
A serious eye injury.
•
Thin areas of the peripheral retina, such as lattice
degeneration.
•
Older age, and some eye conditions such as advanced
diabetic eye disease or inflammation.
If you have
risk factors, follow your ophthalmologist's advice about check-ups, which may
include regular dilated examinations. Know the warning signs, and seek urgent
care if they appear even if a recent examination was normal.
Emergency Eye Care or Retina Specialist: Which Do You Need in Vadodara?
If you have
warning signs now, you need same-day assessment, not a routine appointment.
Sattva Eye Hospital's website advises calling its emergency number, +91 75760
82474, for urgent concerns such as sudden vision loss, injury or severe pain.
Its listed OPD hours are Monday to Saturday, 11:00 AM to 8:00 PM, and its
website gives conflicting information about Sunday, so please call and confirm
timings. If you cannot be seen promptly, go to the nearest hospital emergency
department.
If you have
no urgent symptoms, a non-emergency retina consultation suits an existing
diagnosis, follow-up after a treated retinal tear or detachment, high
short-sightedness, a past eye surgery or a family history. A retina specialist
is an ophthalmologist who focuses on disorders of the retina and vitreous.
Sattva Eye
Hospital's retinal
and diabetic eye care page lists dilated fundus examination, retinal
imaging and OCT scans (when required). Its vitrectomy and
retina surgery page describes vitrectomy for retinal detachment repair in
its retina unit, and says a B-scan may be used when blood or cataract blocks
the view. Ask which treatments suit your eye.
Frequently Asked Questions About Retinal Detachment
What are the first warning signs of retinal detachment?
A sudden
increase in floaters, new flashes of light, or a dark curtain or shadow over
part of your vision. Sudden blurring or loss of side vision can also occur.
Can retinal detachment happen without pain?
Yes. Retinal
detachment is usually painless, so the absence of pain does not mean your eye
is safe.
Do flashes and floaters always mean retinal detachment?
No. Most are
harmless, but new or suddenly increased floaters and flashes need an urgent
examination because only a dilated eye exam can tell the cause.
Is retinal detachment an emergency?
Yes. Seek an
eye examination the same day, or go to the nearest hospital emergency
department if you cannot be seen promptly.
Can retinal detachment be treated?
Yes. Surgery or
laser treatment is usually needed, and the method depends on the type, size and
location of the problem. Treatment works best when it is done early.
Can vision return after retinal detachment surgery?
It can improve,
but results vary and cannot be guaranteed. They depend on how long the retina
was detached, whether the macula was involved and other eye conditions.
Who is at higher risk of retinal detachment?
People with a
previous detachment, a family history, significant short-sightedness, past eye
surgery or injury, or thin areas of the retina.
When should I see a retina specialist in Vadodara?
Seek emergency
assessment immediately for warning signs. A non-emergency retina consultation
suits follow-up of an existing diagnosis or a risk review advised by your eye
doctor.
Conclusion: Act Quickly on Warning Signs
Sudden
floaters, new flashes, a curtain or shadow, or sudden vision loss can signal a
retinal tear or detachment. Because they are not always dramatic and rarely
cause pain, treat them as urgent and get examined the same day. If your eyes
feel fine but you have risk factors, ask your ophthalmologist about regular
checks.